Blog article
Twin Pregnancy: Why Closer Monitoring Is Needed
Twin pregnancies are not one uniform group. Placental and sac arrangements shape risk, scan planning and the conversations needed throughout pregnancy.
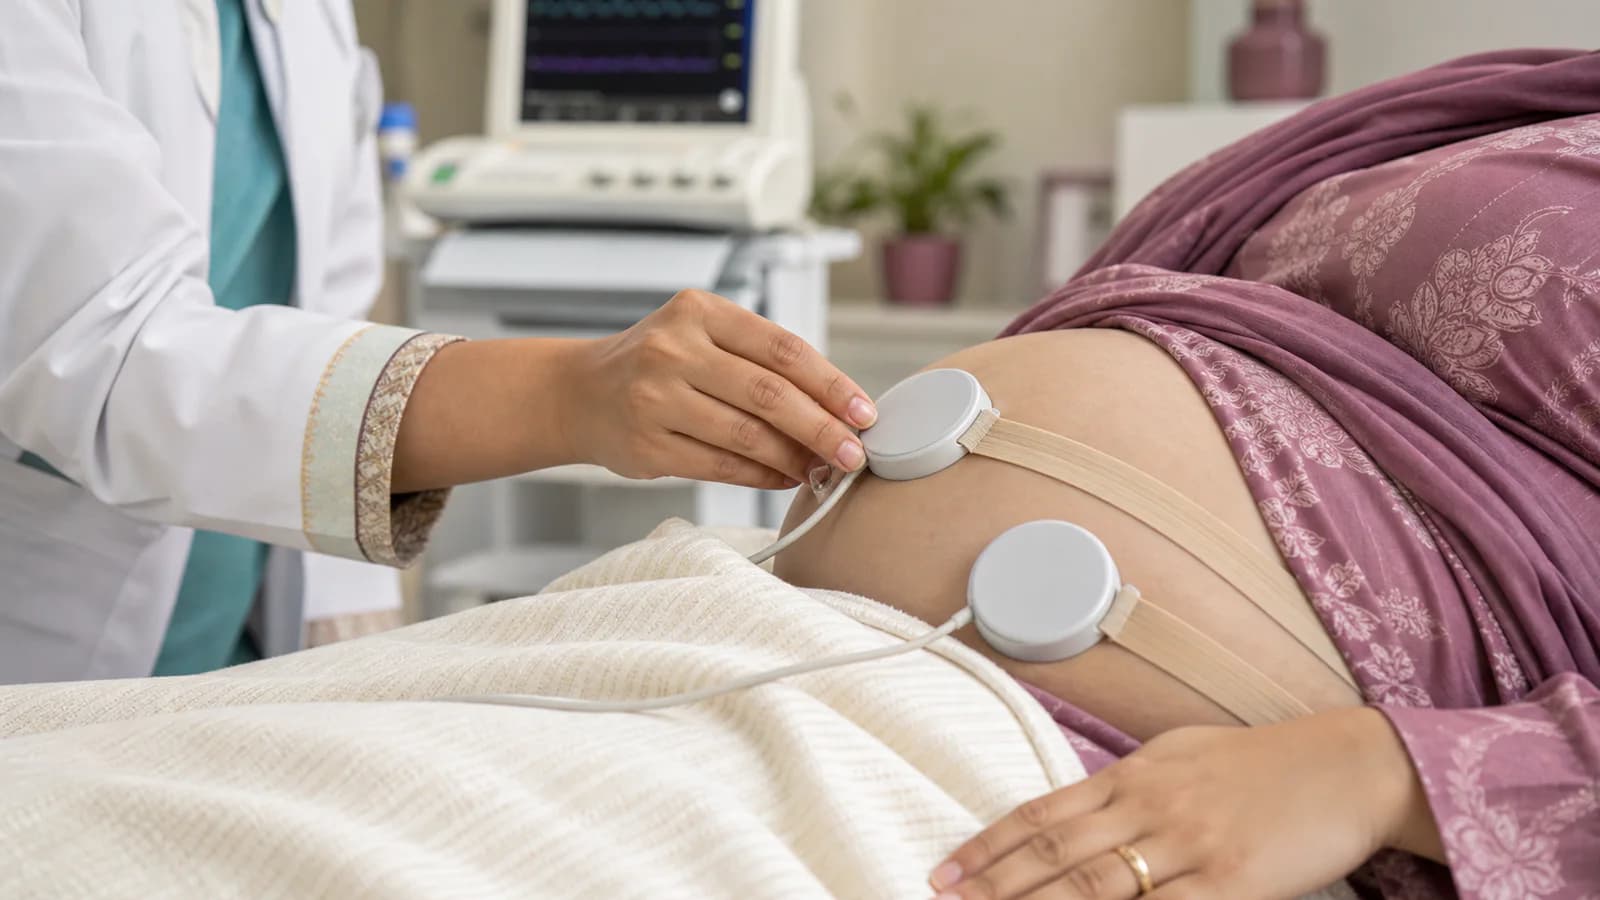
Why twin pregnancy needs a specific care pathway
A twin pregnancy places different demands on the mother and requires surveillance for complications that are less common in a singleton pregnancy. The amount of monitoring is not identical for each twin pregnancy. Placental sharing, amniotic sacs, growth patterns, symptoms and maternal conditions determine the care plan.
Closer monitoring is preventive. It aims to identify growth differences, preterm-birth risk, blood-pressure disorders, anaemia and complications linked to a shared placenta. Extra appointments do not mean a problem has already occurred. They create opportunities to detect change early and plan birth in an appropriate facility.
Chorionicity and amnionicity matter
Chorionicity describes whether twins have separate placentas or share one, while amnionicity describes whether they have separate amniotic sacs. These features are assessed by ultrasound, ideally early in pregnancy when the signs are easier to interpret. The result should be documented clearly and used consistently throughout care.
Shared-placenta pregnancies are monitored for complications such as twin-to-twin transfusion syndrome and selective fetal growth restriction. Assessment for twin anaemia–polycythaemia sequence is added in defined situations or according to the specialist monitoring protocol. Not every uncomplicated twin pregnancy follows the same surveillance schedule.
Scan schedules are individualized
Ultrasound monitoring looks at fetal growth, fluid and other features relevant to the type of twin pregnancy. Shared-placenta pregnancies generally need more frequent assessment than pregnancies with separate placentas. Complications, growth differences or abnormal Doppler findings can increase the frequency further.
This is why one scan timetable copied from another twin pregnancy can be unsafe. The obstetric team should explain the chorionicity, what each scan evaluates and when referral to fetal-medicine expertise is appropriate. Missed appointments should be rescheduled promptly rather than waiting until the next routine date.
Growth and preterm-birth concerns
Twins are more likely to be born preterm and may grow at different rates. Ultrasound estimates are interpreted as trends, not exact weights. The team may assess estimated weight difference, fluid and blood-flow measurements. A difference does not automatically mean immediate delivery; its size, progression, gestation and other findings matter.
Symptoms such as regular painful tightenings, leaking fluid, pelvic pressure or bleeding need prompt assessment because they may signal preterm labour. Routine bed rest is not recommended. Any medicine or activity restriction should be used only for an individualized clinical reason.
Maternal health and nutrition
Twin pregnancy is associated with increased risk of anaemia, hypertension, pre-eclampsia and gestational diabetes. Antenatal care may include additional blood counts, blood-pressure review and glucose assessment according to local guidance. Severe headache, vision change, upper abdominal pain, sudden swelling or breathing difficulty needs urgent evaluation.
Nutrition should support the increased demands of pregnancy without a rigid “eat for three” message. Protein, dietary variety, iron and other nutrients may need attention. Nausea or reflux can make large meals difficult, so smaller meals may help. Supplement doses and aspirin or other preventive medicines must come from the treating team.
Fetal movement and warning symptoms
Discuss how to monitor fetal movement with the obstetric team because perceptions may differ in twin pregnancy. A clear reduction or concerning change needs direct assessment. Home devices cannot establish fetal wellbeing and should not delay care. Bleeding, fluid leakage, severe pain, fever, breathlessness or seizures also require urgent evaluation.
Know which maternity unit to attend, especially if specialist neonatal support may be needed. Keep pregnancy records and the documented twin type available. Routine messaging channels are not suitable for emergencies or reduced movement.
Delivery planning for twins
Timing depends on chorionicity, amnionicity, growth, complications and local guidance. Mode of birth also considers the presentation of the first twin, gestation, size difference, previous birth history, maternal preference and the team’s expertise. Twin pregnancy does not automatically require caesarean birth, and vaginal birth cannot be promised.
Planning should include place of birth, neonatal facilities, fetal monitoring, pain relief and the possibility that the route changes after labour begins or after the first twin is born. A senior obstetric discussion can explain the proposed timing and the situations that would bring birth forward.
Families can ask whether neonatal admission is likely, how two babies will be identified and monitored, and what feeding support is available if birth is early. A tour or written explanation of the unit may reduce uncertainty. Plans for transport, help at home and recovery are especially useful when appointments and newborn care will involve two infants.
Emotional wellbeing also deserves attention. Repeated scans and discussions of risk can create anxiety even when results are reassuring. Ask the team to explain changes using plain language and to distinguish routine twin surveillance from a finding that needs intervention. Counselling or peer support may help without replacing clinical care.
Frequently Asked Questions
What is chorionicity?
Do twin pregnancies follow one scan schedule?
Do twins require caesarean birth?
When should reduced fetal movement be assessed?
Sources and References
These authoritative sources support the educational statements in this article. They do not replace personalised assessment or medical advice.
- National Institute for Health and Care Excellence: Twin and triplet pregnancy (NG137)Published 4 September 2019Last updated 9 April 2024Checked 29 July 2026
- World Health Organization: WHO recommendations on antenatal care for a positive pregnancy experiencePublication year 2016Checked 29 July 2026
- Centers for Disease Control and Prevention: Urgent Maternal Warning Signs and SymptomsPublished 15 May 2024Checked 29 July 2026
High-risk pregnancy care
Explore closer monitoring and coordinated pregnancy care.
Delivery planning
Prepare for shared decisions about timing and mode of birth.
Pregnancy warning signs
Review symptoms that need prompt assessment.
Related articles
Delivery Planning: Vaginal Birth, Caesarean Birth and Shared Decisions
A birth plan is a shared clinical conversation, not a promise. Learn how vaginal and caesarean birth options are considered and why plans may change.
High-Risk Pregnancy: Warning Signs and Essential Care
A reassuring guide to high-risk pregnancy warning signs, closer monitoring, and how essential care helps protect mother and baby.
Pregnancy Nutrition: Practical Guidance for a Healthy Pregnancy
Pregnancy nutrition is not about a perfect menu. It is a practical pattern of varied food, safe preparation and individualized support for changing needs.